because prevention is better than cure.

because prevention is better than cure.

Mini Cart 0

Your cart is empty.

Mini Cart 0

Your cart is empty.

Brain Fog: How to Clear the Mist of Your Mind

In this article, we will explore how to get rid of brain fog and discuss practical strategies to help you regain mental clarity.

by Patrick Holford and edited by Nuala Mcdermott

Brain fog article image of cloud over the face

Have you ever experienced ‘brain fog’?

Difficulty concentrating, feeling mentally sluggish, forgetful, and unable to focus or think clearly?

Increasingly, the term “brain fog” is used to describe a range of cognitive symptoms that affect mental clarity and sharpness. Although brain fog isn’t a medical diagnosis, it is often a sign that your brain isn’t functioning at its best. The encouraging news is that many of the underlying causes are modifiable, meaning there are practical steps you can take to improve your mental clarity and support long-term brain health.

Is your brain running out of energy?

Our brains require a constant supply of energy to function optimally, just as our bodies do. Typically, this energy comes from glucose. However, as we age, or in those experiencing cognitive decline, the brain can become less efficient at using glucose. This reduced ability to access energy is often linked with insulin resistance, leaving brain cells effectively “hungry“. When brain cells don’t receive enough fuel, they struggle to perform efficiently, which may contribute to symptoms such as poor concentration, mental fatigue, forgetfulness, and what many people describe as brain fog. It can also leave you craving sugary foods as your brain searches for a quick source of energy.

One way to address this is by improving the brain’s ability to use alternative fuels. A lower glycaemic load diet, and for some people, a lower carbohydrate or Hybrid Diet approach, may help encourage the production of ketones, an alternative fuel that the brain can use efficiently. One practical way to increase ketone production, without following a strict ketogenic diet, is through C8 MCT oil.

Mind the gap with C8 oil

This energy deficit can be filled by an alternative fuel: ketones, which are made from C8 oil, a type of medium-chain triglyceride (MCT). Coconut, palm, and, to a lesser extent, olive oil all contain MCTs. However, recent research has shown that almost all ketones are made from a specific fraction of these fats called C8. Unlike other fats, C8 is rapidly converted by the liver into ketones, providing an alternative energy source that the brain can readily use.

Research by Dr Melanie Fortier and Professor Stephen Cunnane from Sherbrooke University (1,2) has shown that C8 oil can dramatically boost brain energy levels, particularly in those with cognitive decline. In studies involving people with Alzheimer’s disease or mild cognitive impairment, those who consumed C8 oil experienced an impressive 230% increase in brain energy derived from ketones, leading to significant improvements in memory, language skills, and overall cognitive function.

“People with cognitive decline have an energy gap,” says Professor Cunnane. “Probably due to insulin resistance, they are not able to make use of glucose. Providing a food source, C8 oil, from which the body can readily make ketones, fills that energy gap. Brain cells come back to life, and memory and brain function improve as a result. It reminds me of those announcements on the London Underground, ‘Mind the gap.’“

By filling this energy gap with ketones, C8 oil may not only help improve mental clarity and cognitive function but also reduce sugar cravings. When the brain has a steady, reliable source of energy, it no longer sends out urgent signals for quick fixes like sugar, helping to restore balance and mental clarity.

In Professor Cunnane’s study, participants were given 30 g, approximately two tablespoons, of predominantly C8 oil each day. It is virtually tasteless and is often best taken with food, although many people simply add it to their morning coffee. If you’re new to C8 oil, it’s sensible to start with a small amount and gradually build up over several days to allow your digestive system to adapt.

Omega-3 and B vitamins – the dynamic duo

Supporting your brain’s energy supply is only part of the picture. For brain cells to communicate efficiently, repair themselves, and continue producing energy, they also need the right nutrients. Two of these important nutrients are omega-3 DHA and B vitamins, which work together to support healthy brain function.

In recent years, researchers have discovered that omega-3 and B vitamins are co-dependent, meaning they work most effectively together. This led to a study (3) in which people with mild cognitive impairment were given either folic acid (800 mcg), omega-3 DHA (800 mg), or both nutrients together for one year and compared with those receiving placebos.

The individual nutrients each showed some cognitive benefits, but the greatest improvements were seen in those taking both omega-3 DHA and folic acid together. The combination produced significant improvements in all three measures of IQ, including full, verbal, and performance IQ, demonstrating a clear advantage for people experiencing cognitive decline.

Researchers from Tianjin Medical University and Hebei Medical University in China also investigated the effects of these nutrients on mitochondria, the tiny energy factories inside every cell. They found that participants taking the nutrients had less oxidative damage to mitochondrial DNA. (3)

“The cognitive benefits might act via DNA oxidative damage and mitochondrial function,” they reported.

Healthy mitochondria are essential for keeping brain cells functioning efficiently. When mitochondrial energy production declines and oxidative stress increases, brain cells can struggle to meet their energy demands, potentially contributing to brain fog, poor concentration, and mental fatigue.

The researchers concluded that: “Interventions of folic acid (800 mcg) combined with DHA (800 mg) daily orally for 12 months can improve cognitive function in older adults with Mild Cognitive Impairment, and the combined intervention is superior to either intervention alone.“

Folate is found naturally in green leafy vegetables, while DHA is found primarily in oily fish and other marine foods. However, the amounts used in this study would be difficult to obtain through diet alone, highlighting why targeted supplementation may sometimes be appropriate. Learn about supplements that support brain function

Could your diet be contributing to brain fog?

It’s not only a lack of energy or nutrients that may contribute to brain fog. Researchers worldwide (4,5,6,7) have identified that, in some individuals, food intolerances may also contribute to symptoms including brain fog, anxiety, and depression.

The reasons are complex, but researchers are increasingly linking digestive health with brain health through what is known as the gut-brain axis.

Our gut contains more immune cells than the rest of the body combined. Inside our 10-metre digestive tract live around 100 trillion bacteria, weighing approximately 2 kg and made up of around 130 different species, collectively known as the gut microbiome.

Excessive consumption of inflammatory foods, including refined sugars, ultra-processed foods, alcohol, trans fats, and, for some individuals, gluten, may disrupt this delicate ecosystem. This can reduce populations of beneficial bacteria such as Lactobacillus and Bifidobacterium, while encouraging the excessive growth of less beneficial bacteria that promote inflammation.

Inflammatory foods may also increase the production of zonulin, a protein that affects the tight junctions between cells lining the gut wall. This can increase intestinal permeability, often referred to as “leaky gut“, allowing undigested food particles, toxins, and microbes to pass into the bloodstream, where they may trigger ongoing immune activation and inflammation.

Because the brain and gut communicate continuously through the gut-brain axis, inflammation originating in the gut may influence neurotransmitter production, immune signalling, and brain function. For some people, this may contribute to symptoms such as brain fog, poor concentration, low mood, and anxiety.

Food intolerances are only one possible contributor to brain fog, and they are unlikely to be the cause for everyone. However, if symptoms consistently worsen after eating particular foods or digestive symptoms accompany brain fog, it may be worth exploring this further with a qualified healthcare practitioner or experimenting with eliminating certain foods for short periods of time to see if there is an improvement.

Other considerations if brain fog persists

Brain fog is rarely caused by a single factor. If improving your diet and supporting your brain’s energy don’t fully resolve your symptoms, there are several other areas worth investigating.

Vitamin D

Vitamin D is an all-rounder when it comes to brain and mental health. It supports neurotransmission, helps regulate inflammation, and has important neuroprotective effects by reducing both inflammation and oxidative stress within the brain. Low vitamin D levels have also been linked with poorer cognitive performance and mood in many studies. If brain fog is an ongoing issue, checking your vitamin D status is well worth considering. Find out more about vitamin D’s role in brain health.

Homocysteine, omega-3 and B vitamins

We also know that people with depression often have much higher homocysteine levels, indicating poorer methylation, together with significantly lower levels of vitamin B12 and vitamin D. The levels of these nutrients have been shown to predict the severity of their symptoms (9).

Homocysteine is one of the most important, yet overlooked, biomarkers for long-term brain health. Elevated levels may indicate that your body isn’t recycling homocysteine efficiently, often because of suboptimal levels of folate, vitamin B12, or vitamin B6.

If brain fog or other symptoms of cognitive decline persist, testing homocysteine, together with omega-3 and vitamin D, can provide valuable insight into your nutritional status. These are all included in our DRIfT blood test.

Order your DRIfT blood test.

Prioritise sleep

Sleep is another essential consideration because it is during sleep that many of the brain’s repair and maintenance processes take place.

During deep sleep, the circulation of blood and cerebrospinal fluid improves, helping to remove waste products generated through normal brain metabolism. These include damaging oxidants and amyloid proteins associated with Alzheimer’s disease, both of which can begin to accumulate after even one night of sleep deprivation.

If you regularly wake feeling unrefreshed or rely on caffeine simply to function, improving sleep quality may be one of the most effective ways to reduce brain fog and restore mental clarity.

Read more about improving your sleep.

Steps to reduce brain fog

  1. Support your brain with C8 oil

    If you decide to try C8 oil, begin with a small amount, such as one teaspoon once or twice daily, and gradually increase as tolerated. Many people eventually build up to around one tablespoon twice daily.
    One delicious way to enjoy C8 is Patrick’s Hybrid Latte, combining unsweetened almond milk, almond butter, two tablespoons of C8 oil, one teaspoon of unsweetened cacao, and half a teaspoon of cinnamon.
    You can also stir C8 into smoothies, add it to meals, or simply mix it into your morning coffee

  2. Consider a lower glycaemic load

    Supporting stable blood sugar levels throughout the day may help improve both energy and mental clarity. We recommend a lower glycaemic load approach for most people because it helps provide the brain with a steadier supply of energy.
    If you’d like practical guidance on putting this into practice, then make sure you get access to our brain upgrade programme – COGNITION. It takes you step by step through the principles and details of low glycaemic load eating, so you learn how to build brain-friendly meals. It takes the guesswork away, and you get access to this when you become a FRIEND of Food for the Brain.
  3. Test, don’t guess

    Rather than guessing which nutrients you might need, consider measuring them.
    Testing your vitamin D, omega-3, and homocysteine levels can help identify nutritional imbalances that may be contributing to brain fog, allowing you to take a more targeted approach. You can learn more about these assessments and find recommended testing options on the Food for the Brain Tests page.

  4. Take the Cognitive Function Test

    Use our FREE validated Cognitive Function Test to assess your current brain health and discover practical, personalised steps you can take to support your cognition and reduce your future dementia risk.

  5. Learn more

    If you’d like to understand the science behind brain health in greater depth, Patrick Holford’s book Upgrade Your Brain brings together over four decades of research into nutrition, lifestyle, and cognitive function, with practical strategies to help optimise your brain throughout life.

Final thoughts

Brain fog shouldn’t simply be accepted as an inevitable part of getting older or living a busy life. It is often your brain’s way of telling you that something needs attention. Whether the underlying cause is poor brain energy, unstable blood sugar, nutrient deficiencies, chronic inflammation, or poor sleep, identifying and addressing those factors can make a meaningful difference to how you think, feel, and function every day.

As more research continues to emerge, these practical steps can help set you on the path towards a sharper mind, better focus, and long-term brain health.

References
  1. Croteau E, Castellano CA, Richard MA, Fortier M, Nugent S, Lepage M, Duchesne S, Whittingstall K, Turcotte ÉE, Bocti C, Fülöp T, Cunnane SC. Ketogenic Medium Chain Triglycerides Increase Brain Energy Metabolism in Alzheimer’s Disease. J Alzheimers Dis. 2018;64(2):551-561. doi: 10.3233/JAD-180202. PMID: 29914035.
  2. Danan A, Westman EC, Saslow LR, Ede G. The Ketogenic Diet for Refractory Mental Illness: A Retrospective Analysis of 31 Inpatients. Front Psychiatry. 2022 Jul 6;13:951376. doi: 10.3389/fpsyt.2022.951376. PMID: 35873236; PMCID: PMC9299263.
  3. Karakuła-Juchnowicz H et al (2017) The role of IgG hypersensitivity in the pathogenesis and therapy of depressive disorders. Nutr Neurosci 20:110-8; see also Karakula-Juchnowicz H et al (2018) The Food-Specific Serum IgG Reactivity in Major Depressive Disorder Patients, Irritable Bowel Syndrome Patients and Healthy Controls. Nutrients 10:548; 
  4. Hardman G and Hart G, 2007: Dietary advice based on food-specific IgG results. Nutrition and Food Science 37, 16-23;

Further info

Good Omega-3, Homocysteine & Vitamin D Status Cuts the Risk of Dementia to a Quarter.

by Patrick Holford

There is a reason why we don’t just talk about the benefits of omega-3, or encourage people to only focus on vitamin D – many of these nutrients work synergistically and are all needed to work together to maximise the reduction in dementia risk.

A few months ago, a study looked at three blood tests – homocysteine, vitamin D and omega-3 index and assigned a score of 1 = bad or 0 = good to each result. A person scoring 3 (three ‘bad’ results) had 4.6 times the risk of having dementia compared to a score of 0 (three ‘good’ results). This confirms the synergistic effect of two of our four ‘biological horsemen of the mental health apocalypse’ – brain fats (omega-3 and vitamin D) together with homocysteine-lowering B vitamins. 

The researchers, led by Dr Annike van Soest in Holland say: 

“The effect size we observed was substantial; a four-fold increased risk of developing dementia in individuals with combined suboptimal status of omega-3, vitamin D, and homocysteine (three ‘bad’ results). This effect size is large in comparison with other risk factors of dementia. In our sample, being a current smoker or having diabetes doubled the risk, and being a carrier of at least one APOE ε4 allele (gene variant) tripled the risk of dementia (1).”

In this study, which is the third of its kind, if homocysteine was above 8mcmol/l, that was ‘high risk’ (scoring 1) and if below this, ‘low risk’ (scoring 0). Similarly, if vitamin D was below 15 ng/ml (37.5 nmol/l) that was classified as high risk and if the omega-3 index was below 5%, then that was classified as high risk. 

Interestingly, this was based on the research of risk according to blood levels. So, while it is already known that if homocysteine is above 11mcmol/l the brain is shrinking at an accelerated rate, in this study, even levels above 8 are associated with increased risk of dementia! 

At Food for the Brain, we set the optimal level for homocysteine at 7 or less.

Buy Blood test here button.

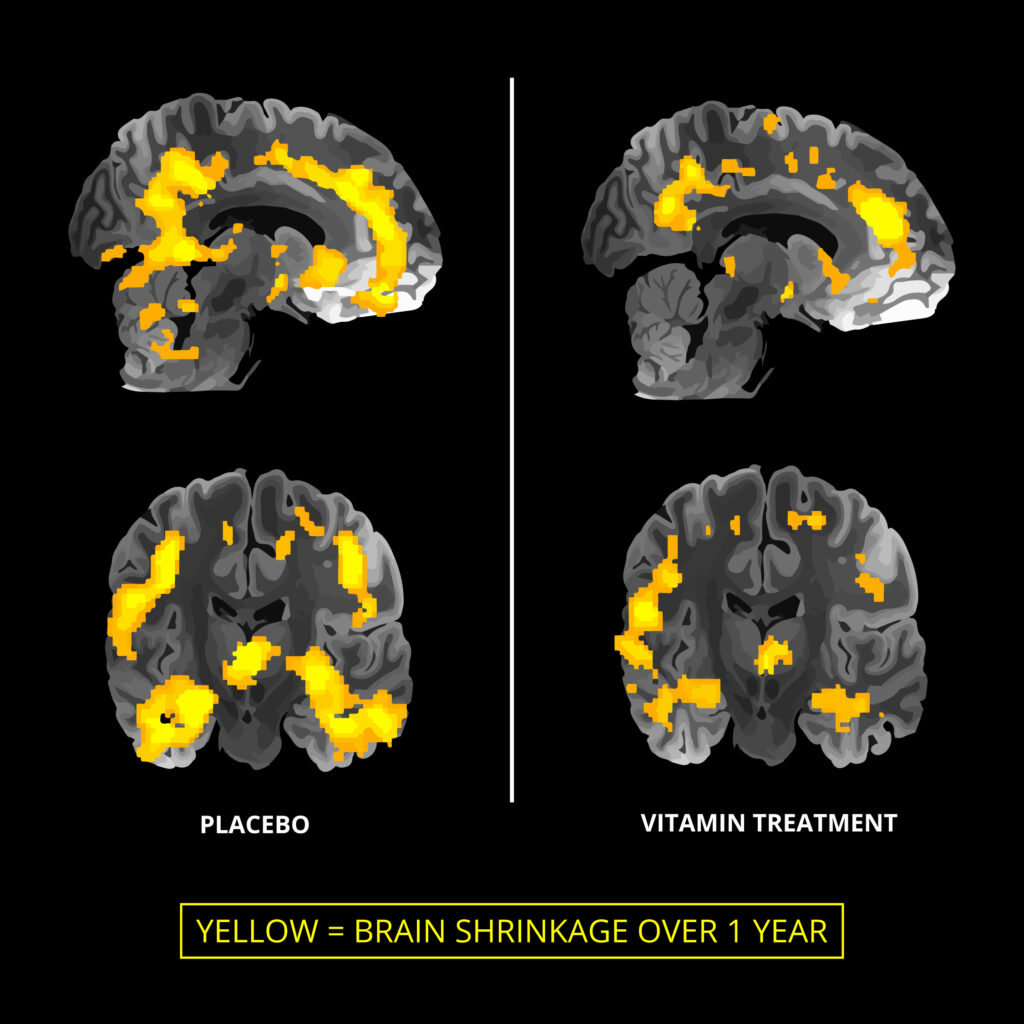
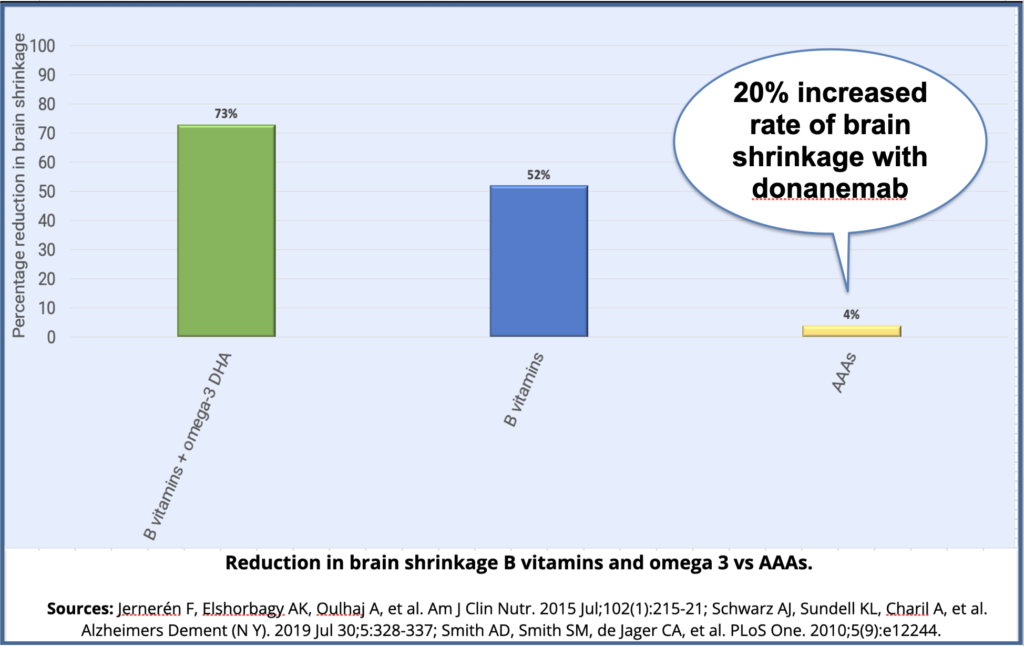
According to Professor David Smith from Oxford University whose group carried out the original study of this kind, homocysteine-lowering B vitamins slowed the rate of brain shrinkage by 73%. They also slowed the rate of cognitive decline, arresting it in a third of trial participants.  

He stated: 

“For too long nutrition has been relatively discounted as a factor in the causation of dementia. This study corrects that misconception and lays the foundation for prevention based upon multiple nutrients.”

A study in France (2), which didn’t include homocysteine but did include a measure of carotenoids as an indicator of ‘oxidation’ reported a fourfold increased risk if all blood tests were in the ‘high-risk’ category.

We offer a similar range of tests in our Dementia Risk Index functional Test (DRIfT) but with more sensitivity, plus adding in HbA1c as a measure of blood sugar resilience. We have also recently added a Glutathione Index test as a measure of antioxidant status. 

In other words, we are looking at ‘four horsemen of the mental health apocalypse’, not just two. Additionally, instead of only having a good/bad, 0/1 scale we have a four-point scale, from 0 to 3 for each test. So, our 4 in 1 test can score within a range of 0 to 12.

On a practical level, your goal is to have all blood test levels in ‘the green’ zone, which we have set as:

– homocysteine below 7
– omega-3 index above 8%
– vitamin D above 40 ng/ml or 100 nmol/l
– HBA1c below 5.5%;
– Glutathione Index above 800.

Tracking changes in these markers against changes in cognitive function would provide further evidence for a systems-based approach to preventing age-related cognitive decline. Whilst it might sound technical, when you test with us (and support our charity and research in the process), we help by making it clear and easy to understand.

We hope to have substantial test results soon, and to plug into NHS patient data to import more test results for vitamin D and HbA1c, along with future dementia diagnoses. This will help further develop and research the perfect DRIfT score and enhance our guidance for your future protection against cognitive decline.

Exciting, isn’t it?

What can you do?

  • Online test. Find out more about your own brain health and unique risk factors by completing the FREE Cognitive Function Test here
  • Blood Tests. Order one of your at-home pin-prick blood tests here.
    You can find out your homocysteine, vitamin D, HbA1c, Omega-3 and Glutathione index results from your own home worldwide and also contribute to our Citizen Science Research
  • Become a FRIEND and support our charity and get access to COGNITION – your personalised online program to help you reclaim your brain. Become a FRIEND here
  • Get the book! Order the latest Upgrade Your Brain book here if you are in the UK 

References

1.  van Soest APM, de Groot LCPGM, Witkamp RF, van Lent DM, Seshadri S, van de Rest O. Concurrent nutrient deficiencies are associated with dementia incidence. Alzheimers Dement. 2024 Jun 12. doi: 10.1002/alz.13884. Epub ahead of print. PMID: 38865433.

2.  Neuffer J, Gourru M, Thomas A, Lefèvre-Arbogast S, Foubert-Samier A, Helmer C, Delcourt C, Féart C, Samieri C. A Biological Index to Screen Multi-Micronutrient Deficiencies Associated with the Risk to Develop Dementia in Older Persons from the Community. J Alzheimers Dis. 2022;85(1):331-342. doi: 10.3233/JAD-215011. PMID: 34806604.

Further info

Anti-Age & Re-Energise Your Brain – The Glutathione Breakthrough

Anti-Age & Re-Energise Your Brain – The Glutathione Breakthrough

By Patrick Holford

Glutathione Breakthrough

Your brain consumes more energy than any other organ, burning either glucose or ketones. 

This combustion creates oxidants that age your brain. 

The ability to rapidly extinguish these oxidants, which ultimately age your brain and body, is what helps you live longer with less wrinkles, more flexible joints, healthier blood vessels and organs, especially your brain. Your brain has 400 miles of blood vessels. Keeping oxidants down is perhaps the single most important thing you can do for vascular health. Vascular dementia, for example, is strongly associated with oxidation. It is oxidised cholesterol that predicts heart attacks (along with raised homocysteine).

For those who have been following our ‘four horsemen of the mental health apocalypse’, oxidation is the fourth horseman. Check out this film to understand how key antioxidants work together. Those with diets high in antioxidant foods literally halve their risk for dementia compared to those with low intakes, according to a study last year of 2,716 people aged over 60. (1) 

The key antioxidants are vitamins C, E, glutathione, anthocyanidins (in blue/red foods), lipoic acid and co-enzyme Q10. The most important of these are vitamin C and glutathione.

Also, critical antioxidants such as vitamin C and vitamin E, if supplemented together, reduced the risk of developing Alzheimer’s by as much as two-thirds. Taking either, cut risk by a quarter in a study of 4,740 elderly residents of Cache County, Utah. (2) 

A review of all studies to date show, that ‘either a high vitamin E or C intake showed a trend of attenuating risk by about 26 per cent’ according to China’s leading prevention expert Professor Jin Tai Yu of Fudan University in Shanghai, making these nutrients ‘grade 1’ top level prevention factor. (3)

Eating fruit and veg might not be enough…

Now, I’m sure you eat fruit and vegetables and supplement vitamin C but how do you know you’ve optimised your anti-oxidation potential? After all, the variation in antioxidants is 40-fold! Even in organic produce.

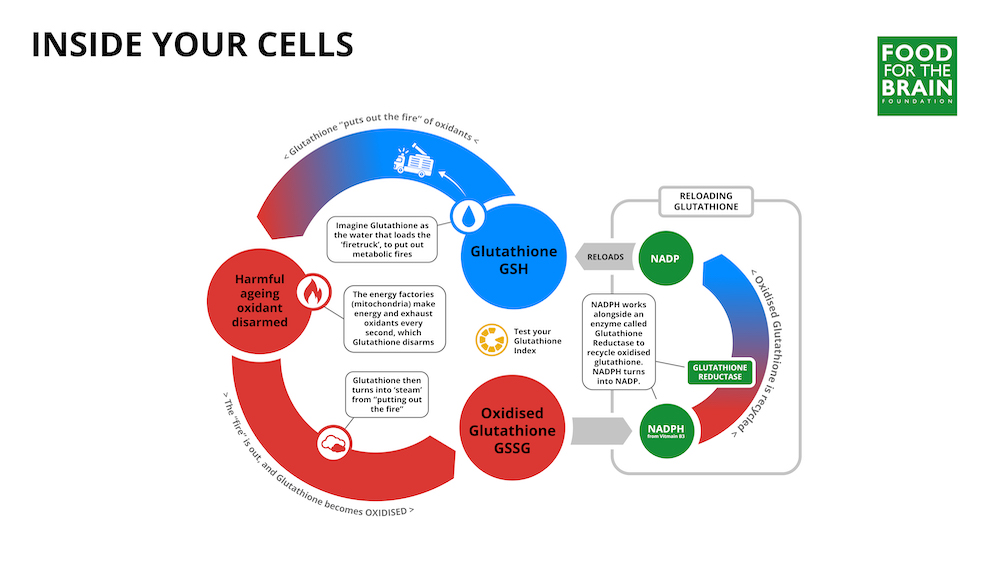
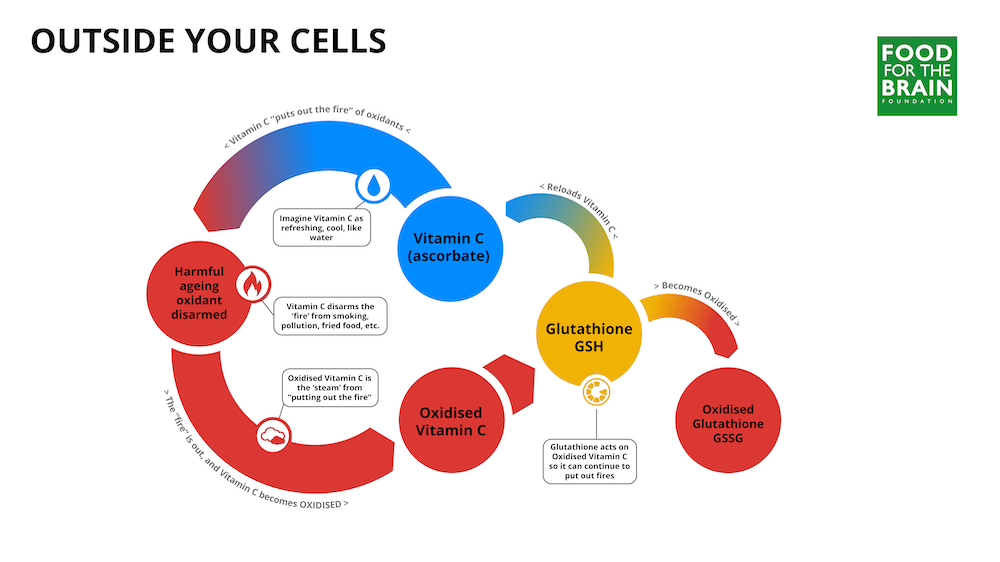
The way in which these harmful oxidants (think of them like mini fires or bursts of heat) are ‘extinguished’ is to effectively ‘cool’ them. Otherwise they bump into things, like arteries, cholesterol, fats and ‘burn’ them setting up a chain reaction of damage. 

That cooling is largely done by either glutathione (GSH) or vitamin C (Ascorbic Acid). They are the firemen. But, when they leave a fire zone they too become hot or oxidised. Oxidised vitamin C is called DiHydroAscorbicAcid, or DHAA. Oxidised glutathione is called GSSG.

Vitamin C helps ‘reload’ glutathione and glutathione helps reload vitamin C as you’ll see in the figures below. This glutathione-vitamin C cycle is one of the hottest discoveries in anti-ageing science. You’ll see that niacin (vitamin B3) and its cousin NAD are involved.

People with cognitive decline and dementia have less glutathione and more oxidised glutathione and an ever decreasing ability to recycle the spent/oxidised glutathione back to functional glutathione. Read the science here. That is why we recommend anyone with concerns about their cognitive health measure their glutathione index.

Your Glutathione Index – a world first!

By measuring a pin prick of your blood in our new test kit both how much glutathione you have in your cells AND how much is oxidised you will know if you’ve got the ability to extinguish those ageing fires in your brain and body optimally. (Technically, it is the ratio between active glutathione (GSH) and spent glutathione (GSSG) or GSH/GSSG.)

So, rather than guess, why not find out by testing your Glutathione Index? 

These at home test kits are now available internationally! (UK, EU, USA & AUS!)

Knowing your Glutathione Index lets us advise you on what you need to eat and supplement to anti-age your brain. This is all included in your ‘interpretation of results’. Your Glutathione Index will also become part of your DRIfT score (Dementia Risk Index functional Test score) – you are aiming for a DRIfT score for ‘0’ which means, biologically, you have a super-healthy brain (and body).

Why other Glutathione tests may not be so accurate and are twice the price

So you are fully in the loop, other labs test red cell Glutathione. This is good but not nearly as good as the ratio of GSH/GSSG. It also tends to cost around £150 and requires a blood draw at a lab.

You want your score to be above 800.

If your score was below 500 that’s really not good. If you smoke, live in a polluted environment or rarely eat fuit, vegetables, herbs and spices, that’s where you’d be.

But we’ve found out something rather disturbing. 

Since glutathione is such a powerful antioxidant the second it leaves your body it starts to oxidise simply from interacting with air. That is why many blood tests, and studies based on them, are not so accurate. We have solved this by adding a super strong ‘fixer’ to the dry blood spot target where you drip your drop of blood. Problem solved!

Thank you for being a Citizen Scientist

When you order your Glutathione test – which you can buy as a single test here OR as part of the DRIfT 5 in 1 test bundle here you can become a part of our team of Citizen Scientists!

You also need to complete your Cognitive Function Test which is FREE and together with any blood test results you get, give you personalised information on what you need to do to optimise your brain AND it will also contribute to our vital research – thank you.

References:

2 Basambombo LL, Carmichael PH, Côté S, Laurin D. Use of Vitamin E and C Supplements for the Prevention of Cognitive Decline. Ann Pharmacother. 2017 Feb;51(2):118-124. doi: 10.1177/1060028016673072. Epub 2016 Oct 5. PMID: 27708183.

3 Yu JT, Xu W, Tan CC, Andrieu S, Suckling J, Evangelou E, Pan A, Zhang C, Jia J, Feng L, Kua EH, Wang YJ, Wang HF, Tan MS, Li JQ, Hou XH, Wan Y, Tan L, Mok V, Tan L, Dong Q, Touchon J, Gauthier S, Aisen PS, Vellas B. Evidence-based prevention of Alzheimer’s disease: systematic review and meta-analysis of 243 observational prospective studies and 153 randomised controlled trials. J Neurol Neurosurg Psychiatry. 2020;91(11):1201-9. Epub 2020/07/22. doi: 10.1136/jnnp-2019-321913. PubMed PMID: 32690803; PMCID: PMC7569385.

Further info

The Lancet Report Omission! World Experts Criticise Latest Alzheimer Report

The Lancet Report Omission! World Experts Criticise Latest Alzheimer Report

The recent Lancet dementia commission has ignored the best nutrition prevention evidence. (See the Lancet Commission Report here)

The Alzheimer’s Prevention Expert Group has accused the Lancet Commission of bad science for knowingly ignoring two highly effective and firmly evidence-based ways to reduce risk factors for dementia – high dose supplements of B vitamins and omega-3 fish oils as well as the impact of a low sugar diet. 

Alzheimer’s prevention  expert group

We support this group of eleven leading scientists and have called on the Lancet to revise their report, which hit the headlines in the past weeks, minimising the effectiveness of nutrition and lifestyle interventions.

(Click here to read the three letters sent to The Lancet asking for a revision in this report.)

The major benefit of B vitamins is their ability to lower levels of the damaging amino acid homocysteine, found in the brain of Alzheimer’s patients. A comprehensive Chinese review of Alzheimer’s prevention research in 2020, described homocysteine lowering as ‘the most promising intervention for Alzheimer’s disease prevention’ (1).

Last month, a review in the Journal of Prevention of Alzheimer’s Disease, listed reducing homocysteine among the top five evidence-based actions (2).  A US National Institutes of Health review attributes almost a quarter (22%) of the risk of Alzheimer’s to raised homocysteine and a further 22% to lack of seafood and omega-3 fish oils (3). 

The combination of high homocysteine, low omega-3 and vitamin D is present in the majority of those over 50 and quadruples dementia risk, according to research in Holland earlier this year, led by Professor Annick van Soest at Wageningen University (4). 

“Remarkably, a suboptimal status of all three nutrients was associated with a four-fold increased risk of dementia,” she says.  These common combined deficiencies, so easily corrected, could have a bigger impact on dementia risk than any of the 14 risk factors listed in the Lancet Commission’s report.

The Lancet Alzheimer Report Omission

Yet, for the third time since the first Lancet Commission report in 2017, and despite being sent all the evidence, the report’s scientists, headed by Professor Gill Livingston, have ignored it. 

Instead, two far less significant risk factors have been added – cholesterol and cataracts. The report claims cataract surgery would eliminate a very modest 2% of overall risk. In stark contrast, reducing high homocysteine, which affects one in two of over 65 ‘s could potentially eliminate a quarter of all risk, “saving the UK economy approximately £60 million per year,” says Oxford University health economist, Professor Apostolos Tsiachristas.

Why has important science been missed out?

Asked why she continued to deny any benefit from homocysteine lowering, Professor Gill Livingston commented: “high homocysteine only affects a small number of people and there are no trials that show that lowering it has any benefit.” 

This is simply not true.

Studies in Holland (5), Norway (6), the UK (7) and China (8), have additionally reported a synergistic effect between B vitamins and omega-3, with several times better clinical benefit than any dementia drug. A study at Oxford University showed two thirds less brain shrinkage in those with mild cognitive impairment given B vitamins with sufficient omega-3 compared to placebo and one third of trial participants were clinically dementia-free at the end of one year (9). These studies were sent to Professor Gill Livingston in 2023.

The commission has also ignored studies showing a benefit from improving omega-3 status by eating fish or taking supplements. The Lancet Report cited only one study linking higher blood levels of omega-3 fatty acids with risk for dementia which concluded that this study provided “compelling evidence for a relationship between long-chain omega-3 fatty acids levels and lower risks for dementia and related outcomes .” 

Essentially, the same conclusions were reached by at least eight other similar studies. “Why were these studies ignored?” asked Professor William Harris of the Fatty Acid Research Institute, a leading omega-3 expert in the US. “The vast majority of adults in the western world have suboptimal blood omega-3 fatty acid levels. Increased consumption of marine omega-3 is safe, simple, cheap and effective.”   

By ignoring these well established, easy to change risk factors the Lancet Commission was able to reduce the claimed preventable risk to 45%. Something that China’s leading prevention expert Professor Jin-Tai Yu of Fudan University in Shanghai strongly disputes. “It may be possible to prevent up to 80% of dementia cases if all known risk factors, including homocysteine lowering B vitamins and omega-3, found in oily fish, were targeted.” he says. 

He was co-author of a study in the journal Nature, together with Oxford University’s leading prevention expert Professor David Smith, analysing data from the UK BioBank which concluded that ‘up to 73% of dementia cases can be prevented.” However, even this may be an under-estimate as this study excluded blood test measures, says Professor David Smith. “This figure could be higher if a person’s omega-3 and B vitamin status, measured by a blood test for homocysteine, were taken into account.”

Homocysteine, omega-3 and vitamin D blood levels attribute 45% of modifiable risk to a deficiency of B vitamins and brain fats. 

The Lancet Omission – what can we do?

That is why we offer our free online Cognitive Function Test. In addition, our accurate, at home pin prick blood tests are available internationally, helping you understand your future dementia risk and what you can do to lower it.

We are ‘citizen science’ in action and gathering independent research on the effectiveness of diet, supplements and lifestyle change that anyone can join. 

Simply put – the cultural bias against nutrition, demonstrated by the Lancet Commission’s omissions, isn’t science-based. 

And it certainly isn’t helping those at risk take easy, positive actions to reduce it.

Action steps

The next steps you need to take to reduce your risk:

References:

1 Yu JT, et al. J Neurol Neurosurg Psychiatry. 2020 Nov;91(11):1201-1209
2 He S.-Y, et al. Prev Alzheimers Dis. 2024 Aug;11:917–927
3 Beydoun MA, et al. BMC Public Health. 2014 Jun 24;14:643
4 van Soest APM, et al. Am J Clin Nutr. 2021 Apr 6;113(4):801-809
5 van Soest APM, et al. Eur J Nutr. 2022 Jun;15:61 3731–3739
6 Jernerén F, et al. J Azheimers Dis. 2019;69(1):189-197
7 Oulhaj A, et al. J Alzheimers Dis. 2016;50(2):547-57
8 Li M, et al. Eur J Nutr. 2021 Jun;60(4):1795-1808
9 Jernerén F, et al. Am J Clin Nutr. 2015 Jul;102(1):215-21
10 Zhang Y, et al. Nature Human Behaviour. 2023;7:1185–1195

Further info

Can Autism Be Reversed? A Published Case Study

Can Autism Be Reversed? A Published Case Study

twin girts study article illustration Can Autism Be Reversed? A Published Case Study

At Food for the Brain, we are committed to exploring the factors that influence brain development, cognitive function and mental wellbeing throughout life. While much of our work today focuses on protecting brain health as we age, we also support research and education on children’s brain development through initiatives such as Smart Kids & Teens.

The question of whether autism can be reversed remains one of the most debated topics in developmental medicine. In this guest article, Simon Martin examines a published case study describing two children with autism spectrum disorder who experienced substantial improvements following a comprehensive programme of nutritional, lifestyle and therapeutic interventions. As a single case study, its findings cannot be generalised to all children with autism, but they raise important questions about the potential role of nutrition, metabolism and environmental factors in influencing symptoms and development, and highlight areas where further research is warranted.

Autism: “reversed” in twins with personalised nutrition, supplements and therapeutic approaches

By Simon Martin – this article was originally shared by IHCAN – shared and edited with permission. 

It’s “kind of a miracle”, says one of the paediatricians consulted in a newly-published case study, as twin girls recover – one, so completely it’s as if she never had autism. 

Research charity Documenting Hope, has published a case study detailing the reversal of severe Autism Spectrum Disorder symptoms in fraternal female twin toddlers.

Diagnosed at 20 months with severe (Level 3) ASD and requiring substantial support, the twins exhibited limited communication, repetitive behaviours, and significant gastrointestinal issues. Realising that conventional approaches were unlikely to help, the parents assembled an intervention focusing on environmental and lifestyle factors. 

In a paper published in the journal Personalised Medicine by a multi-disciplinary team, Dr Chris D’Adamo PhD, (who will be speaking at our Smart Kids & Teens Event in 2025) the charity’s Scientific Director and Principal Investigator and Director of the Centre for Integrative Medicine at the University of Maryland School of Medicine, and his colleagues reported the following stunning results: 

“Both twins showed dramatic improvements on the Autism Treatment Evaluation Checklist (ATEC) . The ATEC measures the effectiveness of autism treatment by assessing  communication, social skills, sensory awareness and more. Autism Treatment Evaluation Checklist (ATEC) scores dropped from 76 to 32 and 43 to 4 (scores below 43 indicate neurotypical), respectively, with stability over six months. The progress of Twin P, whose score dropped to 4 from March 2022 to October 2023, was described as “a kind of miracle” by one of the paediatricians. Dr D’Adamo told the Telegraph, “This twin’s functions are comparable to those who have never had an autism diagnosis”.  

Twin L, who had more severe autism at 20 months, scoring 76 initially, reduced this to 32 a year and a half later. D’Adamo said she “improved dramatically, but not quite as much”.

They also highlighted “the clear environmental and lifestyle influences on ASD that these findings help establish, building upon previous studies revealing the comparatively greater impact of these types of factors than genetics”.

D’Adamo and colleagues do not use the word “cure” in their report, but say the symptoms are unlikely to come back; “Because autism is a developmental condition, one can safely say that once they have overcome the developmental aspects of autism and returned to a typical developmental trajectory, they are very unlikely to exhibit the common symptoms of autism again. Symptoms that could return might be more along the lines of things like anxiety, gastrointestinal issues and sensory issues, but not necessarily the behavioural aspects of autism”.

The team from the University of Maryland and Hope concluded: 

“This case revealed a reversal of the Level 3 Autism Spectrum Disorder diagnoses among toddler twin girls that was achieved primarily through environmental and lifestyle modifications over a two-year period. The twins’ dramatic improvements and diagnosis reversal have persisted for over six months with no signs of regression”.

“What’s more”, says Documenting Hope, “we have learned from the parents that the twins’ ATEC scores have continued to drop below those that were originally published in this paper. This is very exciting news for this family and for the promise of symptom reversal in autism as a viable clinical outcome”.

This is not the first report of a reversal/cure of autism, but certainly the first case where researchers have documented treatment initiated and led by parents. The published paper includes a review of the literature, in which D’Adamo and colleagues detail the many “alternative” approaches that have succeeded, but have been ignored by orthodox medicine, even when published, possibly due to lack of blinding, which is challenging for such interventions. Additionally, they say, a degree of expectation bias is possible and more studies are needed for conclusive results regarding any such interventions, particularly in light of both the diversity of possible causes of ASD and the presentation of symptoms.

The nutritional, supplements & therapeutic approaches

Citing almost 50 previous studies, the Hope team write: “There are limited FDA-approved pharmacological options at present to treat ASD. Accordingly, there have been a number of non-pharmacological interventions tailored to address the underlying environmental and lifestyle risk factors that have demonstrated promising, though not conclusive, improvements in ASD symptoms“. 

These include: 

  • Dietary interventions such as gluten and casein-free, GAPS (Gut & Psychology / Physiology Syndrome), a specific carbohydrate diet, low glutamate and ketogenic.
  • Targeted or personalised dietary supplements such as vitamin D, methylfolate, carnitine, vitamin B12 and other micronutrient supplementation, mitochondrial support, or supplements thought to be relevant to a child’s functional genomic situation. 
  • Addressing other modifiable lifestyle factors and environmental interventions, such as more time in nature, a reduction in exposure to artificial light, and improving indoor air quality, have demonstrated promise.
  • Therapeutic interventions addressing a child’s physical structure and function, such as cranial osteopathy, retained reflex integration, physical therapy, and occupational therapy, have also been associated with improved outcomes among ASD patients.

“While reversal of ASD diagnosis is relatively rare, there have been documented cases in the literature of complete recovery with a multi-modal intervention. One such case achieved reversal of ASD diagnosis through a combination of dietary modifications, probiotics and micronutrient supplementation, and antimicrobials that were personalised to the child’s risk factors, clinical presentation and a variety of laboratory tests”.

The approaches taken for this intervention

The parents gathered support and resources from many places.  They worked with an autism parenting coach, utilising the Child Health Inventory for Resilience and Prevention (CHIRP) survey of the Documenting Hope Project, in addition to resources at Epidemic Answers. They also used Applied Behaviour Analysis (ABA, which is typically recommended for new ASD diagnoses –  find out more here) and speech therapy with the twins.  Additionally, the twins’ parents implemented a rigorous diet and nutrition intervention around the time of diagnosis.

First to go was glutamate – aka MSG – following the principles of the Reduced Excitatory Inflammatory Diet (REID – references can be found here ) developed by PhD biochemist Dr Katherine Reid. Dr Reid is a mother of a daughter “no longer considered on the autism spectrum, which is managed 100% through diet”.

Dr Reid is also the author of Fat, Stressed, and Sick: MSG, Processed Food, and America’s Health. She says: “The Reduced Excitatory Inflammatory Diet (REID) is a food lifestyle focused on reducing excitatory and inhibitory signalling imbalances (ie improving neurotransmitter balance) and reducing inflammation through a balanced whole food approach. Some of the most prevalent excitatory and inflammatory foods are gluten, casein (a class of proteins found in dairy), soy, corn (to a lesser extent) and ready-to-eat or commercially processed foods with various food additives, particularly those containing free glutamate and aspartate. These foods can be problematic because of their high concentration of unbound/free glutamate (glutamic acid). Unbound or free glutamate (aka MSG) is most commonly found in processed foods as a food additive or created as a by-product of commercial food manufacturing processes”. The book is available in our Food for the Brain bookstore: here.

The parents put the girls on a strictly gluten-free, casein-free diet that was low in sugar and had no exposure to artificial colours, dyes, or ultra-processed foods. They emphasised organic, unprocessed, freshly prepared, and home-cooked food from local sources when possible.

The twins took a number of dietary supplements, including omega-3 fatty acids, a multivitamin, vitamin D, carnitine and 5-methyltetrahydrofolate, plus individualised homoeopathic remedies. They also used lab tests and genomic information to select nutritional supplements based on the twins’ DNA.

There were some common findings, such as impaired serotonin metabolism and a recommendation that the girls be fed a diet rich in tryptophan to upregulate serotonin production, as well as consume foods rich in vitamins B12, B6 and folate. Both twins had several genetic variants associated with a higher risk of systemic inflammation.

The mother was advised to feed the children foods that are high in betaine and choline, as well as to supplement with Lion’s mane and resolvins (found in fatty fish). However, each girl also had unique needs. P had variants that suggested an increased need for vitamin D. L had several variants associated with neuroinflammation, oxidative stress and compromised detoxification. Advice was provided to support glutathione production.

Both girls had the most sessions of any intervention with an occupational therapist who focused on the specialised technique of neuro-sensory motor reflex integration developed by Dr Svetlana Masgutova, PhD.

Eventually the parents’ research led them to check their home for air quality, mould and moisture. 

In October of 2022, they brought in a Building Biology Environmental Consultant. The consultant tested the home’s indoor air quality, evaluated possible signs of moisture intrusion, and identified other potential sources of toxicants. Air tests for mould were reported to be “very clean”. However, thermal imaging and moisture metre readings suggested the family was encouraged to further evaluate several areas of the home, which suggested water damage. A window in the twins’ bedroom was one area needing more evaluation.

Both girls were seen by a cranial osteopath. The family decided to pursue osteopathic care for L and not for P. L visited an osteopath at regular intervals in 2023 and saw notable benefits.

Outcomes

Twin L’s ATEC (Autism Treatment Evaluation Checklist) scores improved dramatically, from 76 in March 2022 to 32 in October 2023, and then remained relatively stable at 34 in March 2024. Twin P’s ATEC scores also improved dramatically, from 43 in March 2022 to 4 in October 2023, remaining stable at 4 in March 2024.

“In addition to the twins’ improved ATEC scores, numerous other behavioural and social improvements were noted after the implementation of the interventions”, the paper reports. Both L and P’s eye contact, language, and attention had all improved noticeably by autumn 2022. “This was accompanied by participation in a toddler play group three days per week and ultimately attending pre-school three days per week in Fall 2023″. 

Conclusions & future progress

The University of Maryland team give full credit to the parents’ commitment and drive in achieving these results for their twins. They also acknowledge that this level of complex and sustained treatment may be impossible for many families to take on.

“For instance, the cost of the healthy lifestyle modifications and out-of-pocket costs of care of the numerous practitioners and laboratory assessments in this case would be financially prohibitive to many families. Access to healthy foods and the types of practitioners contributing to this therapeutic approach may also be limited for many families”.

However, they conclude: “It has become increasingly clear that ASD treatment is not one-size-fits-all, and that personalised, multi-modality treatment approaches to help address the total load of stressors are likely required to achieve optimal outcomes”.


This case study does not suggest that all autism has the same underlying causes, nor that every autistic individual requires treatment or wishes to change who they are. Autism is a broad spectrum, and experiences vary considerably from person to person. As a single published case study, its findings cannot be generalised. However, it highlights the possibility that, for some children with complex medical and nutritional needs, identifying and addressing underlying biological factors may contribute to meaningful improvements in health, functioning, communication and quality of life. Further research is needed to determine which approaches may be beneficial, for whom, and under what circumstances.

Through initiatives such as Smart Kids & Teens, alongside our wider work in dementia prevention and lifelong brain health, Food for the Brain continues to explore the evidence on how nutrition and lifestyle may support optimal brain function at every stage of life.

Food for the Brain is a charity dedicated to helping people protect and optimise their brain health throughout life. By becoming a FRIEND for just £50 a year, you’ll support this mission while gaining access to our COGNITION Brain Upgrade Programme, live expert-led webinars, monthly coaching workshops, and practical tools designed to help you put the science of brain health into action.

Other resources:

Further info

Lecanemab – Worst Cost-Benefit Ratio in History?

By Patrick Holford

In terms of a cost-benefit ratio, Lecanemab has to be one of the worst in history.

Reported in the media this week as a ‘breakthrough Alzheimer’s medication’ – is this really the case?

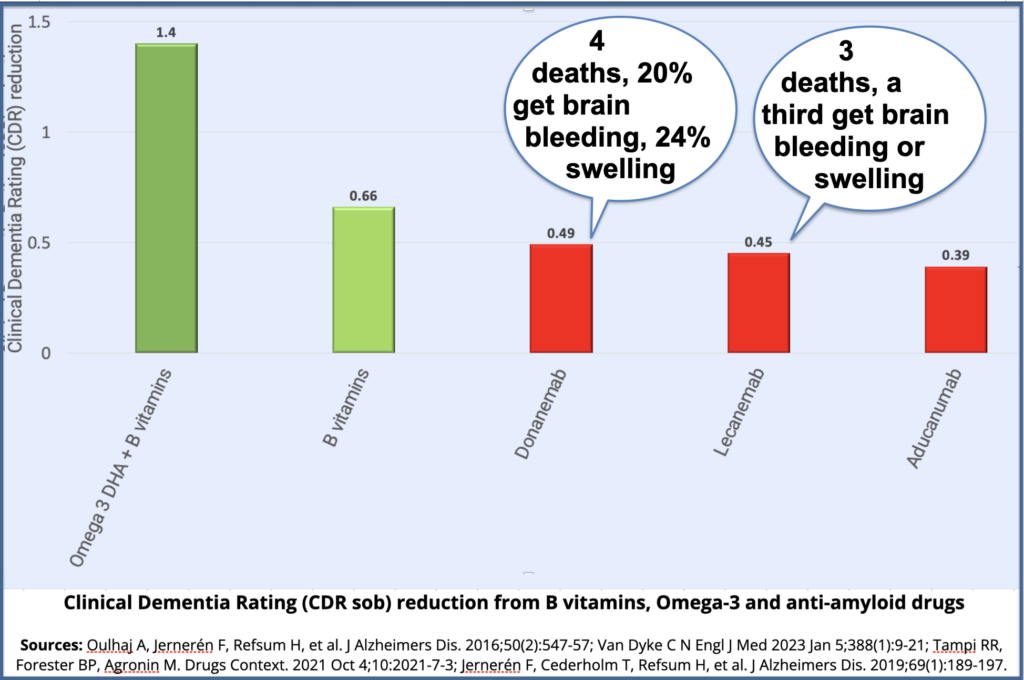
On the benefit side those in the drug company’s own trial got statistically slightly less worse after 18 months of treatment versus placebo. No-one got better. The scale of improvement was not enough to be clinically significant and “does not necessarily reflect a meaningful improvement for patients or their families” according to the British Medical Journal editorial [1]. Given that almost all drug company’s own trial perform better than independent research this is likely to be an over-estimate of benefit not an under-estimate. At best it means delaying the progress of the disease by a few months.

The worst cost is that a quarter of those on the drug got either brain swelling or bleeding.
Three participants in the trial died as a consequence. Also there was accelerated brain shrinkage compared to placebo. Due to these horrendous risks patients getting the twice monthly IV infusions will need to have brain scans to check for brain bleeding and swelling.


The drug itself will cost about £25,000 a year but, with the medical costs, it may actually cost the patients or the NHS as much as double this. That is why the NHS’s watchdog NICE have rejected it “Lecanemab provides on average four to six months’ slowing in the rate of progression from mild to moderate Alzheimer’s disease, but this is just not enough benefit to justify the additional cost to the NHS,” said Helen Knight, director of medicines evaluation at NICE. The Telegraph have stated that an inside source says other anti-amyloid drug treatments would be similarly blocked for NHS use due to bad cost benefit ratio.

The biggest problem…

The biggest lie reported in the papers is that ‘this is the first treatment that has been found to curb the condition’, says the Mail and ‘the first drug to slow down Alzheimer’s”, says the Telegraph.

It isn’t.

Inexpensive and safe B vitamins given to those with raised homocysteine (about half of all over age 65) have produced far greater clinical improvements to those with pre-dementia. In fact, a third had no clinical dementia rating at the end of the year – in other words were no longer diagnosable with dementia.

Similarly encouraging benefits have been shown when omega-3 fish oil supplements have been given to those with already low homocysteine (due to insufficient levels of B vitamins) – up to three times that of Lecanemab.[2] In addition, the omega-3 and B vitamin combo reported up to 73% less brain shrinkage, not more shrinkage reported with this drug. This gold-standard evidence, from studies at the University of Oxford by Professor of Pharmacology David Smith, is simply being ignored.

The choice: safe supplementation or risk of brain bleed…

So, that’s the choice for dementia sufferers.

Safe supplements that might cost you £100 a year, reduce the rate of brain shrinkage and deliver clear clinical improvements. Or Lecanemab, that carries a small risk of death, a considerable risk of brain swelling or bleeding, has not shown improvement in a single patient, but is likely to deliver a small, clinically meaningless slowing down of worsening symptoms. NICE has not approved it for the NHS because it costs £50,000 a year and as it only slows down dementia progression by a couple of months (as reported by the BBC).

The caveat for the drug is that the risks for those with the ApoE4 gene variant – about a quarter of people are deemed too high. The caveat for the B vitamins is that those with normal homocysteine levels (below 10 mcmol/l), which is less than half those over 65, may not benefit from the B vitamin treatment. Homocysteine is a simple test any GP can do. Similarly, omega-3 fish oils may not benefit those with an omega-3 index above 8% (and highly likely to benefit those with an omega-3 index of 4% or less.)

That is why we recommend those wishing to prevent dementia test both omega-3 index and homocysteine and why we offer accurate, at-home test kits to help you reclaim your brain. When you support our charity by buying a test kit you become one of our Citizen Scientists and take part in our essential prevention-focused research and includes a free online Cognitive Function Test and the COGNITION questionnaire which calculates your future Dementia Risk Index, then advising you how to lower it.

References
[1] BMJ 2022;379:o3010 http://dx.doi.org/10.1136/bmj.o3010
[2] https://foodforthebrain.org/campaigns/alzheimers-prevention/omega-3-
and-b-vitamins/

Further info

Drugs Won’t Prevent Dementia

by Patrick Holford

Drugs won’t prevent dementia.

Last week’s Lancet Commission on dementia prevention is facing mounting criticism, for favouring targets for drugs including lowering cholesterol and amyloid and completely ignoring quick and easy wins such as supplementing omega-3, homocysteine lowering B vitamins and reducing sugar intake. A very recent report from Cambridge University scientists says that the benefits of new anti-amyloid treatments may be outweighed by the costs and risk of side-effects such as shrinking brain matter.

US National Institutes of Ageing researcher Dr Madhav Thambisetty warned that trial participants lost up to three teaspoons of brain volume. ‘It is far from clear these drugs can ever significantly reduce dementia morbidity at scale’ report the scientists in the journal Alzheimer’s and Dementia and reported in the Telegraph this week.

The Lancet Commission completely ignored, for the third time since 2017, the indisputable evidence that inexpensive B vitamins, given to those with raised homocysteine (half the older population) reduced brain shrinkage in a year by up to 73%, the highest effect being in those with sufficient omega-3 DHA, as well as the substantial evidence in favour of omega-3.

Our scientists in the Alzheimer’s Prevention Expert Group are actively preparing response letters to the Lancet – and once done, we will give a full report. Against this backdrop of minuscule effect that ‘is so small it would not be recognisable by doctor or patient’ and the need for specialist brain scans with each injection due to one in four getting brain bleeding or swelling we see press-mongering dressing up drugs as prevention; press reports ‘big up’ these unethical drug approaches, as yet unlicensed in the UK, in the guise of prevention – ‘UK needs Covid-style push on dementia drugs’  reports the guardian.

Prevention does not mean drugs, it means tackling the root causes of cognitive decline and brain shrinkage, which is what we are doing at Food for the Brain through our FREE Cognitive Function Test.

“We sent them the indisputable evidence and they ignored it.” Here’s how the Lancet Commission halved the true impact of dementia prevention, says our Founder, Patrick Holford.

Further info

Folic Acid and Methylation Myths: Facts, Fallacies and What the Evidence Suggests

Folic Acid and Methylation Myths: Facts, Fallacies and What the Evidence Suggests

If you have spent any time reading about folic acid, methylfolate, MTHFR or methylation, you have probably come away with more questions than answers. One article claims folic acid is essential. Another insists it is harmful. Some suggest everyone should switch to methylfolate, while others argue the difference barely matters. It is no surprise that so many people end up confused.

The reality is more interesting than either extreme. Much of the debate comes from taking a small piece of biology and stretching it into sweeping conclusions that the evidence does not support. Genes, nutrients and metabolism do interact in fascinating ways, but they rarely fit into simple “good versus bad” stories.

Much of the discussion around folic acid, methylfolate, MTHFR and homocysteine has become increasingly polarised. This article examines several common misconceptions and reviews what the current evidence actually shows.

If you are new to the topic, start with our guide to methylation and homocysteine first. This article is designed as a deeper companion that challenges common misconceptions and adds context to the finer details.

Why Homocysteine Matters in the Folic Acid Debate?

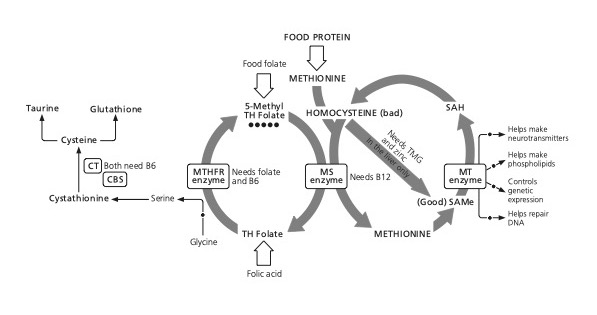
Homocysteine is an intermediary sulphur-containing amino acid generated during methionine metabolism. Under physiological conditions, it is either remethylated to methionine or irreversibly metabolised through the transsulphuration pathway. These reactions depend on an adequate supply of folate, vitamin B12, vitamin B6 and other methylation cofactors.

Because homocysteine reflects the functional efficiency of one-carbon metabolism, it is widely used as a functional biomarker of methylation capacity and folate status. Much of the debate surrounding folic acid, methylfolate and MTHFR variants centres on their effects on these metabolic pathways and, consequently, on homocysteine concentrations. Homocysteine should therefore be interpreted within the broader context of one-carbon metabolism, nutritional status and individual genetic variation, rather than as an isolated biomarker.

Methionine and methylation cycle diagram
Methionine and methylation cycle

Fallacy 1: Folic Acid Doesn’t Work

One of the most persistent misconceptions in nutritional medicine is that folic acid is ineffective and that only methylfolate should be used. This is not supported by the evidence. Folic acid has consistently been shown to lower homocysteine, both on its own and in combination with vitamins B6 and B12. In studies I have reviewed, the beneficial effect on homocysteine is seen regardless of whether an individual carries the common MTHFR C677T polymorphism.

This does not mean that folic acid is always the optimal choice. Folic acid must first be converted into its biologically active form through a series of enzymatic steps. Variations in genes encoding these enzymes, particularly DHFR and, to a lesser extent, MTHFR, can reduce the efficiency of this process in some individuals. However, reduced enzyme activity should not be confused with an inability to utilise folic acid. For most people, particularly those of European ancestry, folic acid remains an effective way to support methylation and lower elevated homocysteine.

There is good evidence that methylfolate raises red blood cell folate more efficiently and lowers homocysteine more effectively than folic acid. In some studies, methylfolate has reduced homocysteine by around 40 to 50% more than an equivalent dose of folic acid. This makes methylfolate a sensible choice where available, particularly for individuals with reduced DHFR activity or those who respond poorly to folic acid.

The important distinction is that saying methylfolate may be superior is not the same as saying folic acid does not work. The scientific evidence does not support that conclusion. For the majority of people, folic acid effectively supports one-carbon metabolism and lowers homocysteine, while methylfolate may provide additional benefit in specific clinical or genetic circumstances.

Fallacy 2: Everyone Needs Methylfolate

Methylfolate is the biologically active form of folate and bypasses the enzymatic steps required to convert folic acid into its active form. As a result, it has been shown to raise red blood cell folate more effectively and lower homocysteine more than equivalent doses of folic acid. This has led some practitioners to recommend methylfolate in preference to folic acid for everyone.

However, the evidence does not support such a universal approach. For most people, folic acid is effectively converted into methylfolate and successfully supports methylation. Numerous intervention studies have shown that folic acid, particularly when combined with vitamins B6 and B12, lowers homocysteine regardless of MTHFR C677T genotype.

There are, however, circumstances in which methylfolate may offer advantages. Individuals with reduced activity of the DHFR enzyme, which is responsible for the first step in folic acid metabolism, may be less able to convert folic acid efficiently. This genetic variation is relatively uncommon in European populations but considerably more prevalent in some Asian populations. In these individuals, methylfolate or folinic acid may represent a more appropriate choice.

The decision should therefore be based on an individual’s nutritional status, genetic background and clinical response rather than the assumption that everyone requires methylfolate. While methylfolate is generally the preferred supplemental form because it bypasses the activation pathway, it is incorrect to conclude that folic acid has no place in clinical practice.

Fallacy 3: MTHFR Means You Can’t Process Folic Acid

One of the most widespread misconceptions is that carrying an MTHFR C677T or TT polymorphism means you cannot process folic acid. This is an oversimplification of how one-carbon metabolism works. The MTHFR enzyme is responsible for converting tetrahydrofolate into 5-methyltetrahydrofolate (5-MTHF), and reduced enzyme activity may influence methylation efficiency, particularly if riboflavin (vitamin B2) status is suboptimal.

The MTHFR C677T polymorphism is common, affecting around 24% of the population overall, although prevalence varies considerably between ethnic groups. Individuals with this variant may have higher homocysteine levels and an increased risk of certain conditions, particularly when B vitamin status is inadequate. However, this does not mean they are unable to utilise folic acid.

Intervention studies consistently show that supplementation with folic acid, particularly alongside vitamins B6 and B12, lowers homocysteine regardless of MTHFR genotype. In other words, people with the C677T or TT polymorphism still respond to folic acid. Ensuring adequate riboflavin status may further support MTHFR enzyme activity in those with these variants.

The presence of an MTHFR polymorphism should therefore be viewed as one factor influencing methylation efficiency rather than evidence that folic acid is ineffective. It may influence the choice of folate supplement in some individuals, but it does not justify the conclusion that everyone with an MTHFR variant is unable to process folic acid.

Fallacy 4: Unmetabolised Folic Acid Is Always Harmful

Another common claim is that the presence of unmetabolised folic acid (UMFA) in the bloodstream is inherently harmful. The reality is more nuanced. UMFA can accumulate when folic acid intake exceeds the body’s capacity to convert it into biologically active folate, particularly in individuals with reduced activity of the dihydrofolate reductase (DHFR) enzyme, which catalyses the first step in folic acid metabolism.

The concern is that unmetabolised folic acid may compete with naturally occurring folate for enzyme binding sites, potentially impairing normal folate-dependent metabolism. This has led to suggestions that excessive folic acid supplementation could, under certain circumstances, induce a functional folate deficiency. However, the likelihood of this depends on both the amount of folic acid consumed and an individual’s genetic capacity to metabolise it.

Reduced DHFR activity is relatively uncommon in European populations but considerably more prevalent in some Asian populations. Individuals with reduced DHFR activity are more likely to accumulate UMFA and may therefore benefit from using methylfolate or folinic acid instead of folic acid. By contrast, there is little evidence that modest intakes of folic acid, such as those typically found in multivitamin supplements, represent a significant concern for most people.

Another area of ongoing research is the relationship between folate and cancer. Folates are essential for DNA synthesis and cell division, meaning they support the growth of healthy cells but may also accelerate the growth of existing pre-cancerous or cancerous cells. While adequate folate intake appears protective before malignant change occurs, excessive folic acid exposure, particularly in susceptible individuals with reduced DHFR activity, may not always be desirable. This remains an area of active investigation rather than settled science.

The practical conclusion is not that folic acid is harmful, but that the form and dose of folate should be matched to the individual. Methylfolate provides the biologically active form without requiring DHFR conversion and may therefore be preferable where reduced enzyme activity is suspected. Nevertheless, the current evidence does not support the conclusion that the presence of unmetabolised folic acid is inherently harmful in everyone.

Fallacy 5: Homocysteine Should Always Be as Low as Possible

Raised homocysteine is associated with an increased risk of numerous chronic diseases and, in most circumstances, lowering an elevated level is beneficial. However, it does not necessarily follow that the lowest possible homocysteine concentration is always the optimal goal.

Homocysteine is not simply a waste product. It is an intermediate metabolite within one-carbon metabolism and also serves as the precursor for glutathione synthesis through the transsulphuration pathway. This pathway depends on the enzyme cystathionine β-synthase (CBS), together with adequate vitamin B6 status. Theoretically, if homocysteine concentrations become extremely low, substrate availability for glutathione synthesis could also be reduced.

In practice, homocysteine concentrations below 4 µmol/L are uncommon, and evidence that very low levels are harmful is limited. Where both homocysteine and glutathione are unusually low, it may indicate impaired folate metabolism or reduced activity of enzymes involved in one-carbon metabolism, such as DHFR or MTHFR, rather than representing an ideal metabolic state.

The key point is that homocysteine should not be interpreted in isolation. It is a functional biomarker that reflects the efficiency of interconnected metabolic pathways and should be considered alongside glutathione status, B vitamin sufficiency and the wider clinical picture. The objective is not to achieve the lowest possible homocysteine concentration, but to support efficient methylation and healthy one-carbon metabolism.

Fallacy 6: More Folate Is Always Better

While maintaining adequate folate status is essential for healthy one-carbon metabolism, more folate is not necessarily better. As with many nutrients, both the form and the dose matter, and the optimal approach depends on an individual’s nutritional status, genetic background and clinical circumstances.

Adequate folate intake supports DNA synthesis, methylation and normal cell division, and sufficient folate status before the development of pre-cancerous changes appears to reduce disease risk. However, once pre-cancerous lesions are established, high circulating folate concentrations, particularly from excessive folic acid supplementation, may accelerate the growth of rapidly dividing cells. This distinction is important and helps explain why the relationship between folate and cancer is more complex than simple claims of benefit or harm.

Individuals with reduced DHFR activity are also more likely to accumulate unmetabolised folic acid when consuming high supplemental doses. In these circumstances, using methylfolate or folinic acid may be a more appropriate strategy than simply increasing folic acid intake. Conversely, for most people, modest amounts of folic acid remain an effective and safe way to support methylation and maintain healthy homocysteine metabolism.

The evidence therefore supports an individualised approach rather than a universal recommendation. The aim should be to achieve adequate folate status using the most appropriate form and dose for the individual, guided wherever possible by biomarkers such as homocysteine and the wider clinical picture, rather than assuming that increasing folate intake indefinitely will produce greater health benefits.

What This Means in Practice

The evidence does not support absolute positions on folic acid or methylfolate. Folic acid remains an effective way to support one-carbon metabolism and lower homocysteine in most people, while methylfolate may offer advantages for some individuals, particularly those with reduced DHFR activity or a poor response to folic acid.

Similarly, the presence of an MTHFR polymorphism should not be interpreted as meaning that folic acid is ineffective or that methylfolate is essential for everyone. Nutritional status, enzyme activity and clinical context are all important considerations when selecting the most appropriate form of folate.

Rather than relying on assumptions or genetic results alone, a more evidence-based approach is to assess functional biomarkers such as homocysteine and interpret these alongside the wider clinical picture. This enables nutritional interventions to be tailored to the individual rather than based on generalisations.

If you’d like to understand the science behind one-carbon metabolism in more detail, explore our Methylation and Homocysteine guide, which explains how methylation works, why homocysteine is such an important biomarker, and how nutrients support these interconnected pathways.

If you don’t know your homocysteine level, consider taking a homocysteine blood test. Homocysteine is one of the most informative functional biomarkers of methylation and brain health, and measuring it provides a practical starting point for understanding your individual nutritional status.

If your homocysteine level is elevated, our evidence-based guide to Lowering Homocysteine explains the role of diet, B vitamins, methylfolate and lifestyle interventions, helping you translate these scientific principles into practical action. ou can also explore our Homocysteine Lowering B Vitamins supplement guide for practical support in putting these strategies into action.

Where appropriate, further investigation, such as testing glutathione status or DHFR genetic variants, may help explain why some individuals respond differently to folic acid and identify when alternative forms of folate may be beneficial.

For those who would like to dig even deeper, these papers are most relevant:

Further info

Four Shocking Facts & Brain-enhancing Opportunities

A message from Patrick Holford, our CEO

Thanks to you, Food for the Brain has grown ten-fold in the last year, reaching another half a million people, with over 20,000 taking the Cognitive Function Test bringing the total to 420,000. In the last three months alone we’ve reached 2 million people and tested the cognitive function of a further 20,000.

Yet, every 3 seconds someone in the world is diagnosed with dementia – in the UK that’s 7 double decker buses worth of people every day. 

At the other end of the spectrum, special needs schools are bursting at the seams as autistic spectrum disorder diagnoses go through the roof. 

Thanks to generous donations from the Fieldrose Trust, Viridian and Heights, we’ve finally built our research database and are beginning to find some interesting things. 

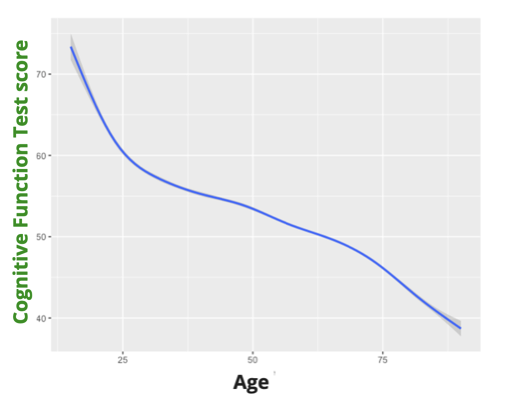
Firstly, cognitive function declines, almost in a straight line, from age 18 to 90+. That’s a completely new discovery! Even 25 year olds have less cognitive function than 20 year olds. That’s why the earlier a person starts to make changes the greater are their chances of never developing dementia. You’ll be pleased to hear that the lower your Dementia Risk Index, calcuated from the COGNITION Questionnsaire you complete as part of the free online test, the better your cognitive function is and people making the changes recommended in the COGNITION programme can REVERSE cognitive decline.

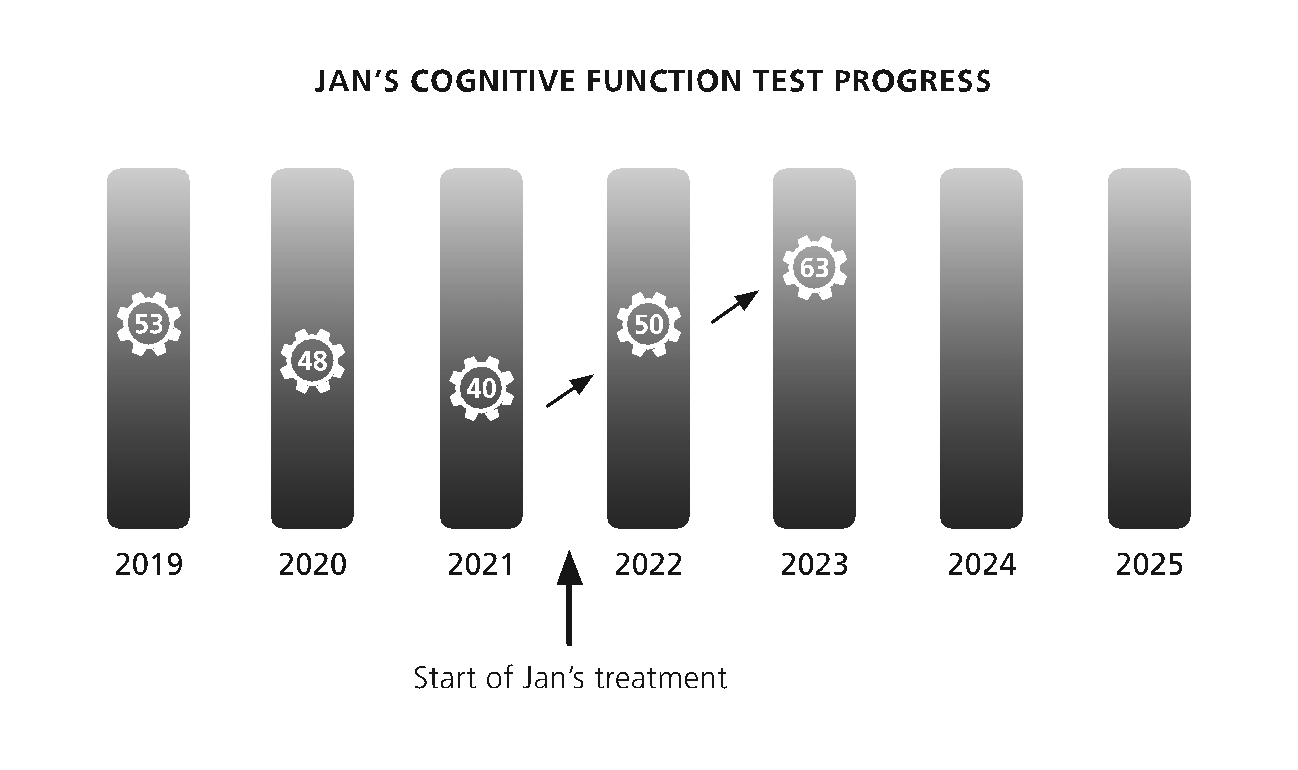
Jan is a case in point. Like the ‘average’ person his cognitive function was declining year on year – until he joined COGNITION. 

Here’s what he says: ‘Food for the Brain’s COGNITION programme has really helped to focus my mind on key changes, a step at a time. Since following their advice, I’m delighted to report that my cognitive function, which was close to the red after 17 months of decline, has returned into the green, better than the average for my age. I had lost my job and my ability to have a productive life, even my ability to speak without long pauses, and any hope of recovery. Food for the Brain’s educational support through COGNITION has demonstrated the potential for recovery such that I now have confidence and increasing hope for the future. Food for the Brain has been my lifeline’. 

Smart Kids – the children are our future

Natalie Coghlan, now appointed as Head of COGNITION for Smart Kids & Teens, is applying everything we’ve learnt from adults to children and teens and is running a small pilot study on 5 to 17 year olds to find out what happens in early years, how we can measure it and – ultimately how we can help children and teens become more mentally and cognitively robust. Please watch this short film from Natalie.

We’ve raised about £5,000 to kick-start this project but need to raise a further £35,000 to see it through to completion. If we can do this, we hope to launch COGNITION for Smart Kids and teens early in 2025. 

That is where SPONSA DONNA comes in.

Donna Von Tunk is sailing around the world and partnering with us so she can raise awareness and funds for this important project. If, collectively, we raise £1 a mile we’ve done it. That means 100 people giving 1p a mile (£400).

Can you help?

>>> Please make a donation and SPONSA DONNA here,
or
>>> Become a FRIEND.

If you’d like to make a more significant donation please contact me at patrick@foodforthebrain.org.

The shocking fact

Now here’s a shocking fact – the Alzheimer’s Society have told us they don’t fund or focus on prevention. 

Nor do Dementia UK. They focus on supporting carers.

Alzheimer’s Research UK allocates less than 4% to non-drug prevention research, despite 80% of Alzheimer’s and dementia being preventable – and none of their current projects are interventions – to find out if a prevention action works for example.

I’m afraid to say it’s drugs all the way, with £5 million going into a study involving testing blood levels of p-tau in 5000 people as a predictor of cognitive decline. That’s £1,000 per person. 

Since testing cognitive function, which we do FOR FREE, is how you diagnose dementia, why not just do this? The most direct way to best predict who is heading for cognitive decline is to test cognitive function itself since it reduces many years before a diagnosis. £5 million would puts 100,000 people through our COGNITION programme helping them to actually dementia-proof their diet and lifestyle. The only logic for this p-tau test is to then say ‘you need the drug’ just as your cholesterol level became the proof that you need statins – which have not worked in any independent study that’s not funded and controlled by the drug makers.

Having failed to find a single UK charity who are taking prevention seriously it really is down to us to drive the prevention action forwards. 

Announcing the COGNITION Biobank project

You’ve probably heard of the UK Biobank. People like me, aged 40 to 69 back in 2006, gave blood, filled in questionnaires and did tests. We are all being tracked to see if we’ll develop dementia or other diseases. No-one is being retested.

Here, at Food for the Brain, we have the COGNITION Biobank. 

If you’ve taken the Cognitive Function Tests you’re part of it. To date we’ve tested 420,000 people AND we encourage you to retest cognitive function every six months or year. Also, we are now encouraging you to test blood levels of key biomarkers such as homocysteine. In this way you become a Citizen Scientist. The UK Biobank didn’t do this, so they never mention homocysteine-lowering B vitamins, which is ‘the most promising treatment’ according to the largest reviews of 396 trials on Alzheimer’s prevention. Also, we ask the right questions in our COGNITION questionnaire because, back in 2006, they didn’t really understand what was driving cognitive decline. 

We hope to have the largest Biobank, specific to cognition, tracking hundreds of thousands of people over time AND encouraging them to make changes by sharing back what works from this research. 

This is science for the people, by the people, funded by the people. 

On that note, we need to raise £1 million, £50,000 at a time to take this project global and big-scale. We are looking for impact investors, with at least £10,000 to invest, with a guaranteed return, much like an ISA. Wouldn’t you rather your invested money was saving people’s brains? Also, unlike other charities where, for every £10 given, £3 goes into fund-raising costs, at Food for the Brain 100% of what you donate goes directly into prevention research and education. We are lean and focused, all working virtually.

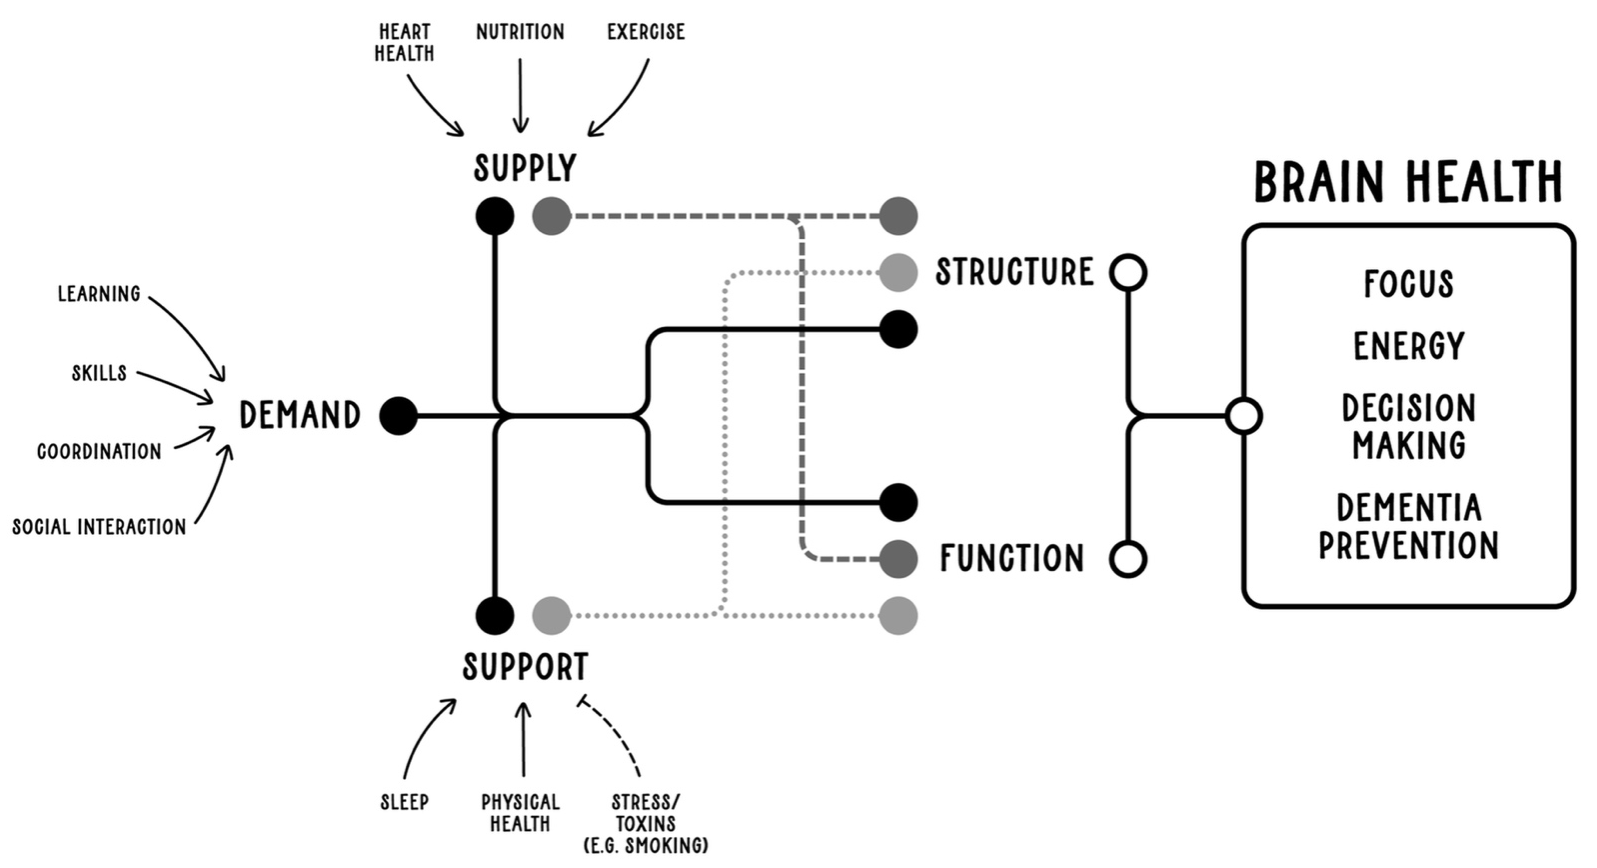
Our Head of Research and Principal Investigator is neuroscientist Dr Tommy Wood, Assistant Professor at the University of Washington. He’s a systems-based thinker and gave an amazing talk at our recent Upgrade Your Brain conference.

You can watch him in action here giving a stunning presentation on a systems-based approach to cognitive function. The diagram below is from his talk. We’ll be publishing a paper on this soon.

A diagram of a structure

Description automatically generated
Prevention is more effective & available right now 

Not only are literally no other charities taking prevention seriously, or keeping up to date with the evidence that is streaming in almost weekly, none have any comprehensive model as to how cognitive decline occurs and how to keep your brain healthy. 

Quoting Alzheimer’s Research UK, whose strapline is ‘we exist for a cure’ they say: “don’t smoke, keep cholesterol and blood pressure under control, be active daily and exercise regularly, maintain a healthy weight, eat a healthy balanced diet, drink fewer than 14 units of alcohol per week.” That’s it. Let’s face it – who didn’t know that? That’s not exactly going to reverse the dementia epidemic. 

Despite part funding the original Oxford trial on B vitamins, which showed up to 73% reduced rate of brain shrinkage, compared to approx. 20% increased brain shrinkage from the latest anti-amyloid drug treatment, their Chief Medical Officer Dr Peter Schott says: “Dietary supplements are big business, and plenty of websites sell vitamins on the promise of boosting brain health. But supplements are only recommended for people with a diagnosed deficiency, and should be taken with a doctor’s support.” 

What on earth does he mean by ‘diagnosed deficiency’? He ignores the fact that about half those over 65 are deficient, indicated by a homocysteine level above 11 mcmol/l. How many doctors even know that, let alone are testing for it? Some test serum B12 but, in the UK, the reference range for this is wrong. In the EU, Japan and Canada if your level is below 500pg/ml you’re deficient. This is correct. In the UK the cut-off level is 180pg/ml. This is wrong. Brain shrinkage is happening below 500 pg/ml. Homocysteine is the most important and predictive test which is why we test it as part of our research. It’s included in the DRIfT test and can be tested on its own – see foodforthebrain.org/tests. Lowering high homocysteine with a 10p a day B vitamin is the single most effective, and cost-effective, prevention action anyone can take. We had it costed by Oxford University’s health economist and found that just this would save £50 million a year in the UK. The next best evidence-based prevention action is to up your omega-3 level (test your omega-3 index here)] to find out how you are doing) and eat a lower carb and low GL diet (glycaemic load goes further than the glycaemic index as it takes into account the portion size of the food). 

Now that would make a difference.

SEEKING A CEO/OPERATIONS DIRECTOR

Having helped shape Food for the Brain’s strategy, and helped it grow exponentially, I need to focus on getting the word out there – teaching as many people, public and practitioners, as possible, getting media coverage, helping spread the word. That’s what I’m good at. In September we launch in Canada, Australia and New Zealand. In November we launch in Japan and China, thanks to generous donations, and I’m going out there to launch the Cognitive Function Test, teach and spread the word. Next we seek donations to translate all this into Spanish and Portugese.

So now we really need a good leader and team player who knows how to get things done, working with our brilliant, highly functional small-but-mighty team. This is a part-time, paid position, with the potential to grow full-time as the charity expands. If you think you might have what it takes and have the combined skills of marketing and operations, digital development and are also able to lead and represent the charity with my full support, plus a background and passion for nutrition and mental health, get in touch by sending your CV to me at patrick@foodforthebrain.org.

Wishing you the best of health and happiness,

A black and white logo

Description automatically generated


—

Further info

WHO says Vitamins B, PUFA (Omega-3) & Multivitamins Should Not Be Recommended

Do supplements really help when it comes to cognitive decline or are they money wasted down the toilet?!

We believe that the science supports the use of correct supplementation in order to reduce risk of dementia and Alzheimer’s – so what is going on and what does the research really say?

The WHO report saying supplements are ‘not recommended’

A 2018 report by the WHO states: ‘Vitamins B and E, PUFA and multi-complex supplementation should not be recommended to reduce the risk of cognitive decline and/or dementia.’ 

This 2018 WHO review makes no reference at all to the effect of B vitamins in slowing brain atrophy (1) and in improving cognition (2) in the rather large sub-group, estimated to be up to half of those over 65, with raised homocysteine. After all, why would B vitamins be expected to have an effect in those not deficient?

On closer inspection, three of the four cited studies in the WHO document are actually one meta-analysis (which is a statistical process of analysing and combining results from several similar studies). It cites only one paper which considered B vitamins (the one part-funded by Alzheimer’s Research UK) which showed a clear effect of B vitamins improving cognition in those with raised homocysteine, and one study on omega-3 DHA, which also shows clear benefit as stated in the studies summaries. Thus, it misrepresented the study that ARUK part funded on B vitamins as negative, when they had a clearly positive effect. 

The only cited B vitamin study (2) states, “The mean plasma total homocysteine was 30% lower in those treated with B vitamins relative to placebo. B vitamins stabilised executive function (CLOX) relative to placebo. There was significant benefit of B-vitamin treatment among participants with baseline homocysteine above the median in global cognition, episodic memory and semantic memory. Clinical benefit occurred in the B-vitamin group for those in the upper quartile of homocysteine at baseline in global clinical dementia rating score… In this small intervention trial, B vitamins appear to slow cognitive and clinical decline in people with mild cognitive impairment (MCI), in particular in those with elevated homocysteine.”

The only cited study on omega-3 fish oils (3) states, “The fish oil group showed significant improvement in short-term and working memory.” The 12-month change in memory was significantly better in the fish oil group. This study suggested the potential role of fish oil to improve memory function in MCI subjects.

So, even based on its own cited evidence, the benefit of both B vitamins and omega-3 fish oils is supported.

How the WHO statement then recommends the opposite, ‘Vitamins B and E, PUFA and multi-complex supplementation should not be recommended to reduce the risk of cognitive decline and/or dementia.’ beggars belief. But the real problem is not the shoddy research, from 2015, used to produce this report but that it is out of date. The WHO ‘rules’ for this report was to ignore any study that was more than 5 years old, yet the WHO authors republished this same report, with the same conclusions, in 2022, by then redundant according to its own rules!

What we’ve learned since 2018

Also, much has been learnt, and published, since 2018. There is now evidence that homocysteine lowering B vitamins are most effective in those with sufficient omega-3 status and omega-3 fish oils are most effective in those with low homocysteine. This is clinical confirmation of the known mechanism of co-dependence and illustrates why the WHO document is now out of date. We prefer published, peer-reviewed reviews such as the editorial in the American Journal of Clinical Nutrition in 2021 (4) and a meta-analysis in 2023 (5).

Additionally, since 2018, there have been at least 17 studies (6-22), including both randomised controlled trials and cohort studies which show benefit of either omega-3 fish oil supplementation, or higher intake from seafood with resultant higher omega-3 blood levels, in reducing risk for and incidence of dementia or cognitive decline.

This is another example showing why the WHO document is no longer current and relevant. Yet leading Alzheimer’s charities such as the Alzheimer’s Society and Alzheimer’s Research UK (ARUK – who part funded the highly effective B vitamin trial) still refer to this redundant report.

With regard to multivitamins, the latest meta-analysis states (7), “The meta-analysis of COSMOS substudies showed clear evidence of multivitamin-mineral benefits on global cognition and episodic memory; the magnitude of effect on global cognition was equivalent to reducing cognitive ageing by 2 years”. B vitamins, given to those with raised homocysteine, are much more effective than multivitamins given to all – and more effecctive in those with sufficient omega-3 status.

Summary

In conclusion, the 2018 WHO report is so sloppy, and out of date – by its own rules. It would be wise for WHO to withdraw this misleading report and certainly for both ARUK and the Alzheimer’s Society and any other Alzheimer’s or dementia organisations to stop referring to it in the context of omega-3, B vitamins or multivitamins, if they are to maintain credibility in being science-based.

Note: Many people are not aware that the WHO is no longer only funded by donations from the countries that it is supposed to serve but is now also privately funded, with the second largest funder being the Bill Gates Foundation, which accounts for 10% of its budget, leading to questions over influences on its agenda. 


References

1. Smith AD, Smith SM, de Jager CA, Whitbread P, Johnston C, Agacinski G, et al. Homocysteine-lowering by B vitamins slows the rate of accelerated brain atrophy in mild cognitive impairment: a randomized controlled trial. PloS one 2010;5(9):e12244.

2. de Jager CA, Oulhaj A, Jacoby R, Refsum H, Smith AD. Cognitive and clinical outcomes of homocysteine-lowering B-vitamin treatment in mild cognitive impairment: a randomized controlled trial. International journal of geriatric psychiatry 2012;27(6):592-600.

3. Lee et al 2013 – https://pubmed.ncbi.nlm.nih.gov/22932777/

4. Smith AD, Jernerén F, Refsum H. ω-3 fatty acids and their interactions. Am J Clin Nutr 2021;113(4):775-8.

5. Fairbairn P, Dyall SC, Tsofliou F. The effects of multi-nutrient formulas containing a combination of n-3 PUFA and B vitamins on cognition in the older adult: a systematic review and meta-analysis. The British journal of nutrition 2023;129(3):428-41.

6. Liu X, Zhuang P, Li Y, Wu F, Wan X, Zhang Y, et al. Association of fish oil supplementation with risk of incident dementia: A prospective study of 215,083 older adults. Clinical nutrition (Edinburgh, Scotland) 2022;41(3):589-98.

7. Vyas CM, Manson JE, Sesso HD, Cook NR, Rist PM, Weinberg A, et al. Effect of multivitamin-mineral supplementation versus placebo on cognitive function: results from the clinic subcohort of the Cocoa Supplement and Multivitamin Outcomes Study (COSMOS) randomized clinical trial and meta-analysis of 3 cognitive studies within COSMOS. Am J Clin Nutr 2024;119(3):692-701.

8. Jerneren F, Cederholm T, Refsum H, Smith AD, Turner C, Palmblad J, et al. Homocysteine Status Modifies the Treatment Effect of Omega-3 Fatty Acids on Cognition in a Randomized Clinical Trial in Mild to Moderate Alzheimer’s Disease: The OmegAD Study. Journal of Alzheimer’s disease : JAD 2019.

9. Rouch L, Virecoulon Giudici K, Cantet C, Guyonnet S, Delrieu J, Legrand P, et al. Associations of erythrocyte omega-3 fatty acids with cognition, brain imaging and biomarkers in the Alzheimer’s disease neuroimaging initiative: cross-sectional and longitudinal retrospective analyses. Am J Clin Nutr 2022;116(6):1492-506.

10. He X, Yu H, Fang J, Qi Z, Pei S, Yan B, et al. The effect of n-3 polyunsaturated fatty acid supplementation on cognitive function outcomes in the elderly depends on the baseline omega-3 index. Food & function 2023;14(21):9506-17.

11. Doughty KN, Blazek J, Leonard D, Barlow CE, DeFina LF, Omree S, et al. Omega-3 index, cardiorespiratory fitness, and cognitive function in mid-age and older adults. Prev Med Rep 2023;35:102364.

12. Loong S, Barnes S, Gatto NM, Chowdhury S, Lee GJ. Omega-3 Fatty Acids, Cognition, and Brain Volume in Older Adults. Brain Sci 2023;13(9).

13. Maltais M, Lorrain D, Léveillé P, Viens I, Vachon A, Houeto A, et al. Long-chain Omega-3 fatty acids supplementation and cognitive performance throughout adulthood: A 6-month randomized controlled trial. Prostaglandins, leukotrienes, and essential fatty acids 2022;178:102415.

14. Andriambelo B, Stiffel M, Roke K, Plourde M. New perspectives on randomized controlled trials with omega-3 fatty acid supplements and cognition: A scoping review. Ageing Res Rev 2023;85:101835.

15. Wei BZ, Li L, Dong CW, Tan CC, Xu W. The Relationship of Omega-3 Fatty Acids with Dementia and Cognitive Decline: Evidence from Prospective Cohort Studies of Supplementation, Dietary Intake, and Blood Markers. Am J Clin Nutr 2023;117(6):1096-109.

16. Grande de França NA, Díaz G, Lengelé L, Soriano G, Caspar-Bauguil S, Saint-Aubert L, et al. Associations Between Blood Nutritional Biomarkers and Cerebral Amyloid-β: Insights From the COGFRAIL Cohort Study. The journals of gerontology Series A, Biological sciences and medical sciences 2024;79(1).

17. Sasaki N, Jones LE, Carpenter DO. Fish consumption and omega-3 polyunsaturated fatty acids from diet are positively associated with cognitive function in older adults even in the presence of exposure to lead, cadmium, selenium, and methylmercury: a cross-sectional study using NHANES 2011-2014 data. Am J Clin Nutr 2024;119(2):283-93.

18. van Soest APM, van de Rest O, Witkamp RF, Cederholm T, de Groot L. DHA status influences effects of B-vitamin supplementation on cognitive ageing: a post-hoc analysis of the B-proof trial. European journal of nutrition 2022;61(7):3731-9.

19. Gao J, Fan H, Wang X, Cheng Y, Hao J, Han S, et al. Association between serum omega-3 PUFAs levels and cognitive impairment in never medically treated first-episode patients with geriatric depression: A cross-sectional study. J Affect Disord 2024;346:1-6.

20. He Y, Huang SY, Wang HF, Zhang W, Deng YT, Zhang YR, et al. Circulating polyunsaturated fatty acids, fish oil supplementation, and risk of incident dementia: a prospective cohort study of 440,750 participants. GeroScience 2023.

21. Chedid G, Malik A, Amangurbanova M, Khraishah H, Welty FK. Docosahexaenoic Acid Levels and Omega-3 Index, but Not Eicosapentaenoic Acid Levels, Are Associated With Improved Cognition in Cognitively Healthy Subjects With Coronary Artery Disease. Arteriosclerosis, thrombosis, and vascular biology 2022.

22. Duchaine CS, Fiocco AJ, Carmichael P-H, Cunnane SC, Plourde M, Lampuré A, et al. Serum ω-3 Fatty Acids and Cognitive Domains in Community-Dwelling Older Adults from the NuAge Study: Exploring the Associations with Other Fatty Acids and Sex. The Journal of nutrition 2022;152(9):2117-24.

Further info